


Removal of malignant tumors with free margins is pivotal in oncological surgery.
To verify the correspondence between the histological growth of colon and rectal adenocarcinomas and how extensively methylene blue diffuses when injected into peritumoral mucosal tissue to understand if the dye margin can guide the correct margin for tumor removal, and also if there is an association between the lymph nodes stained by methylene blue and the presence of metastases.
This study was conducted with 13 patients with colon or rectal adenocarcinoma. Immediately before the operation, all patients underwent colonoscopy and peritumoral methylene blue injection. Radical resection consisted of the removal of the colon or rectum segment beyond the blue-stained margins, in a monobloc, with the meso and regional lymph nodes. Tumor margins, peritumoral lymphatic density, stained margins, and removed lymph nodes were analyzed.
In all operative specimens, tumor-free margins were within the blue-stained area. There was no association between the presence of metastases and the dye in the lymph nodes examined.
Preoperative peritumoral endoscopic injection of methylene blue spreads the dye beyond the limits of colon and rectal adenocarcinomas, determining reliable free margins for tumor resection, but does not indicate the presence of regional lymph node metastases.
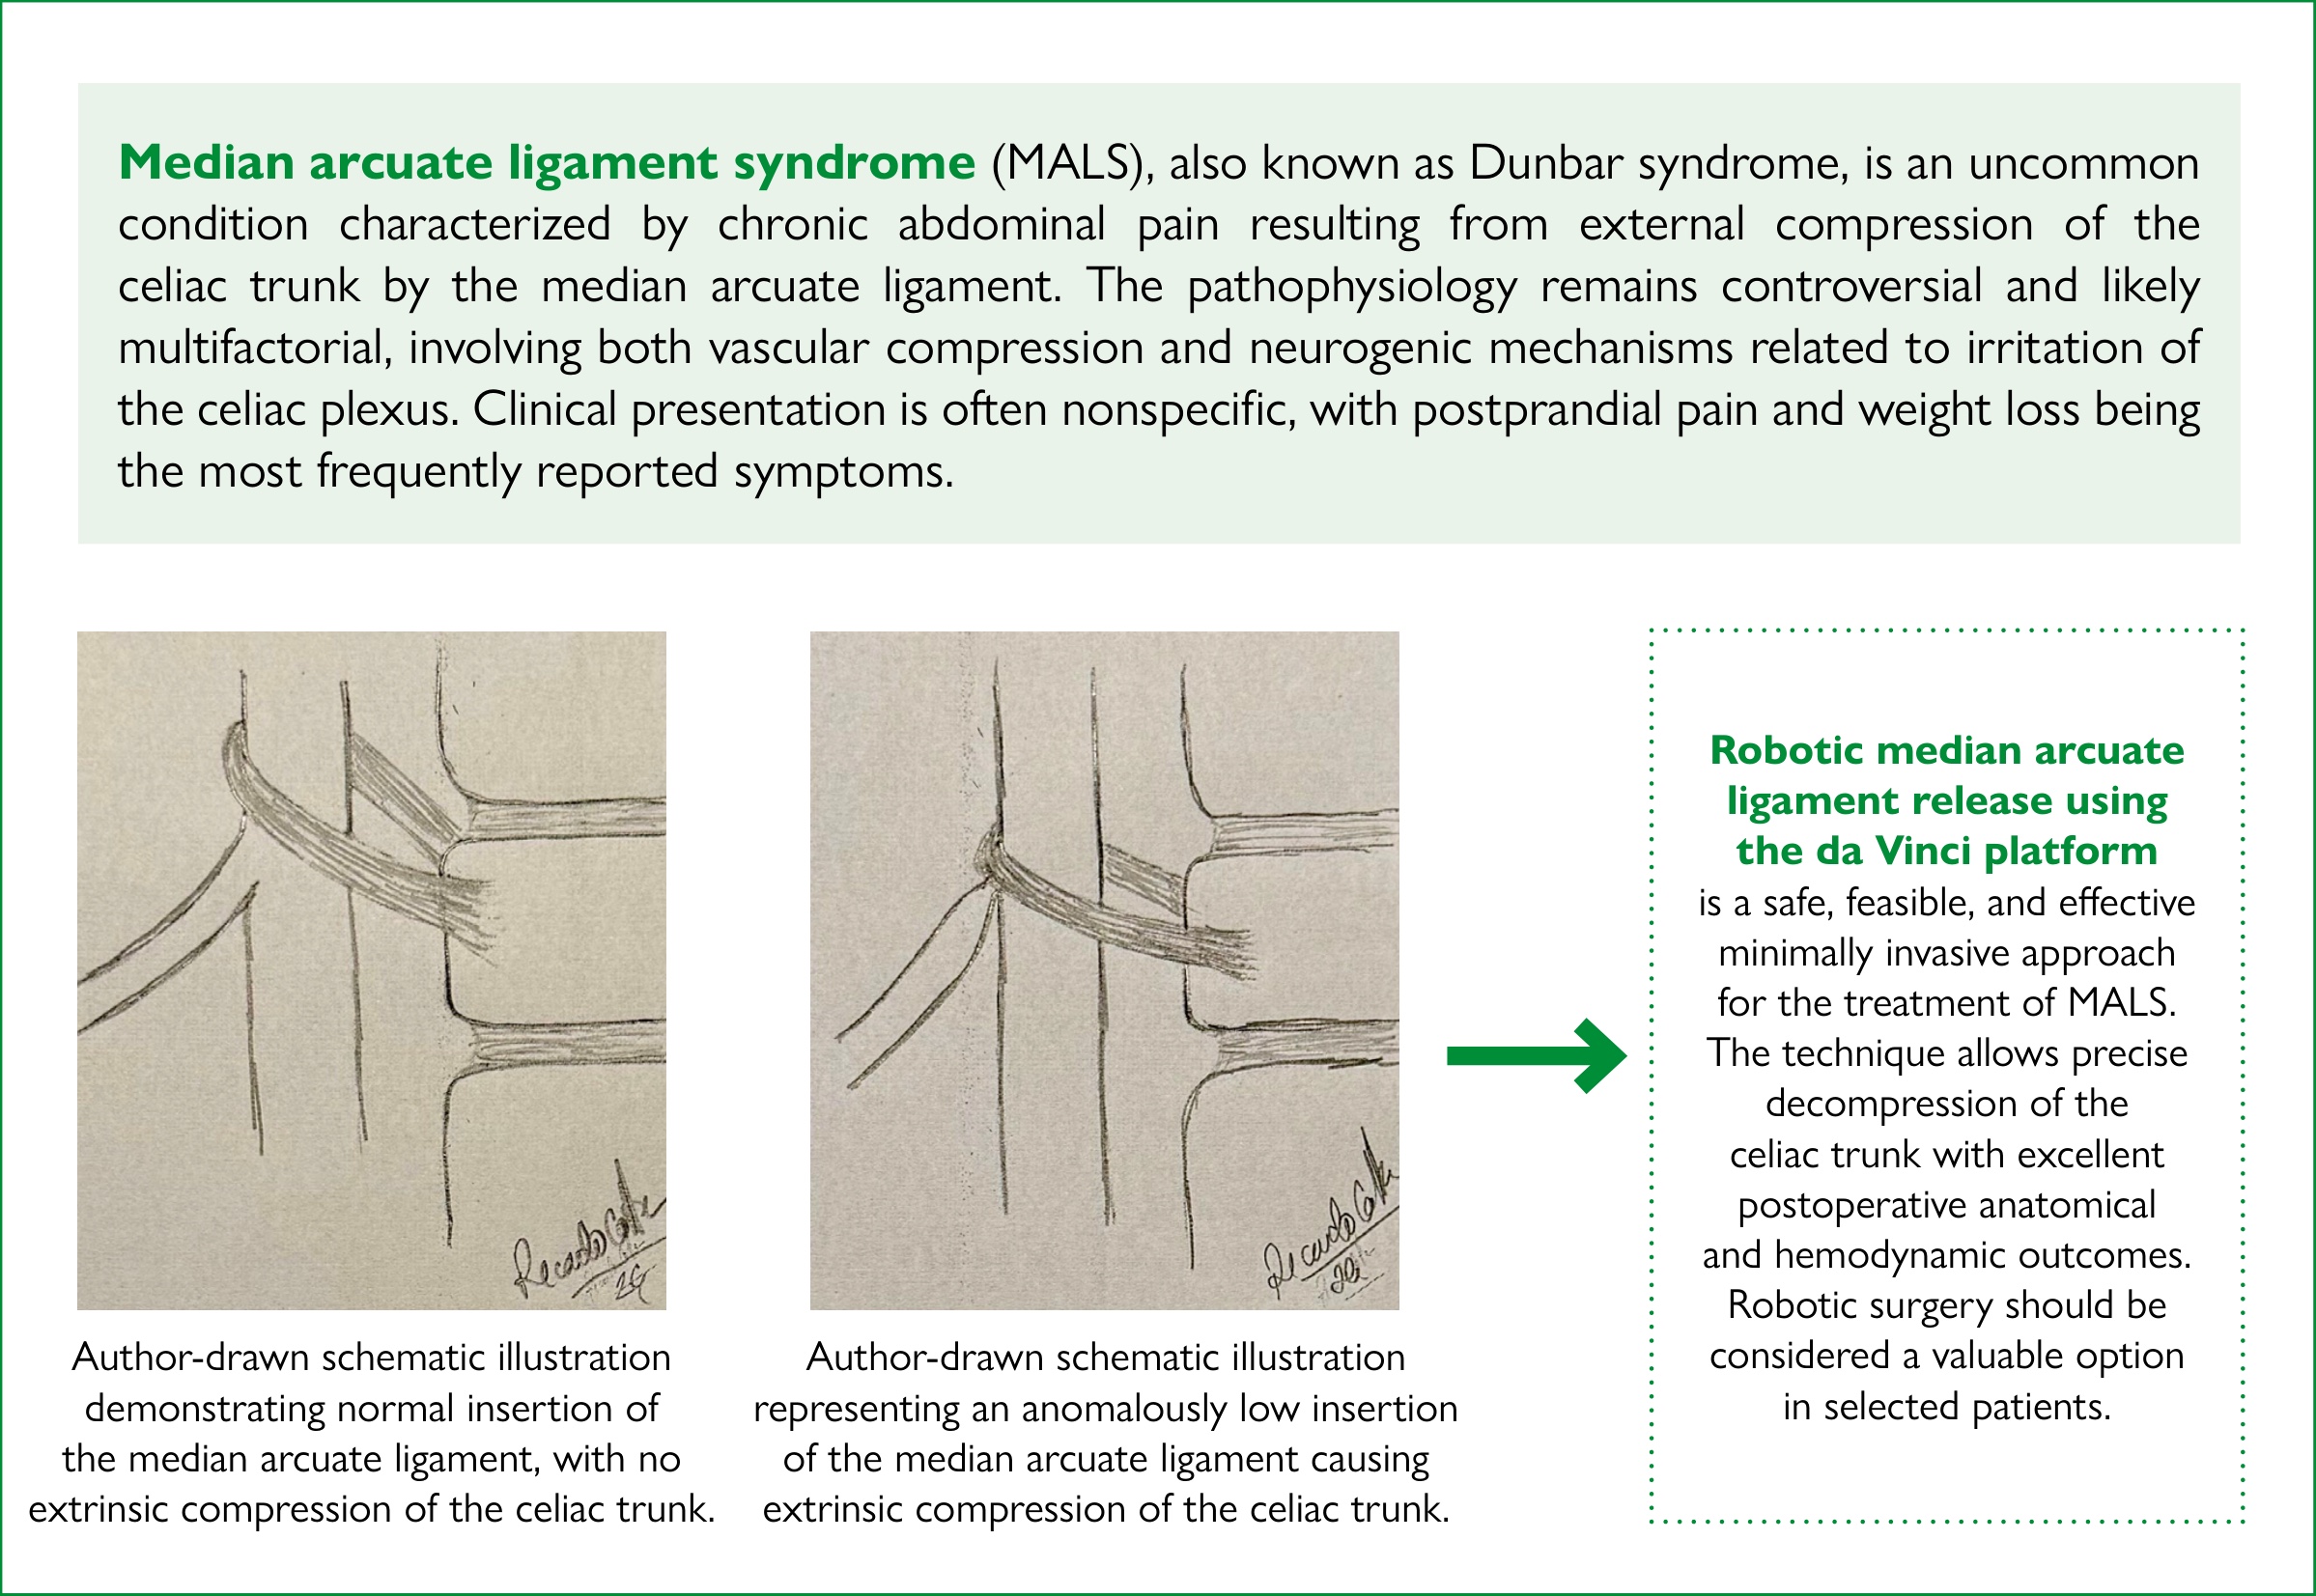
Median arcuate ligament syndrome (MALS) is an uncommon condition characterized by chronic and intermittent abdominal pain, typically postprandial, and weight loss, caused by extrinsic compression of the celiac trunk by the median arcuate ligament. The pathophysiology of the disease is not fully understood. Diagnosis is challenging due to nonspecific symptoms, and requires a careful correlation between clinical findings and imaging studies.
To demonstrate the feasibility, safety, and technical aspects of robotic median arcuate ligament release using a case-based approach with detailed imaging correlation.
The authors report the technical aspects in an elderly male patient with typical symptoms of MALS, who underwent robotic-assisted median arcuate ligament release using the da Vinci X platform. Preoperative evaluation included CT angiography and color Doppler ultrasound, demonstrating focal proximal celiac trunk stenosis.
The robotic approach allowed precise dissection and complete decompression of the celiac trunk without intraoperative complications. Postoperative imaging demonstrated resolution of the stenosis and normalization of Doppler flow parameters. The patient experienced complete symptom resolution, and remained asymptomatic after one year of follow-up.
Robotic median arcuate ligament release is a safe and effective minimally invasive option, providing excellent visualization and precise dissection in a challenging anatomical region. This technique should be considered a valuable approach for selected patients with MALS.
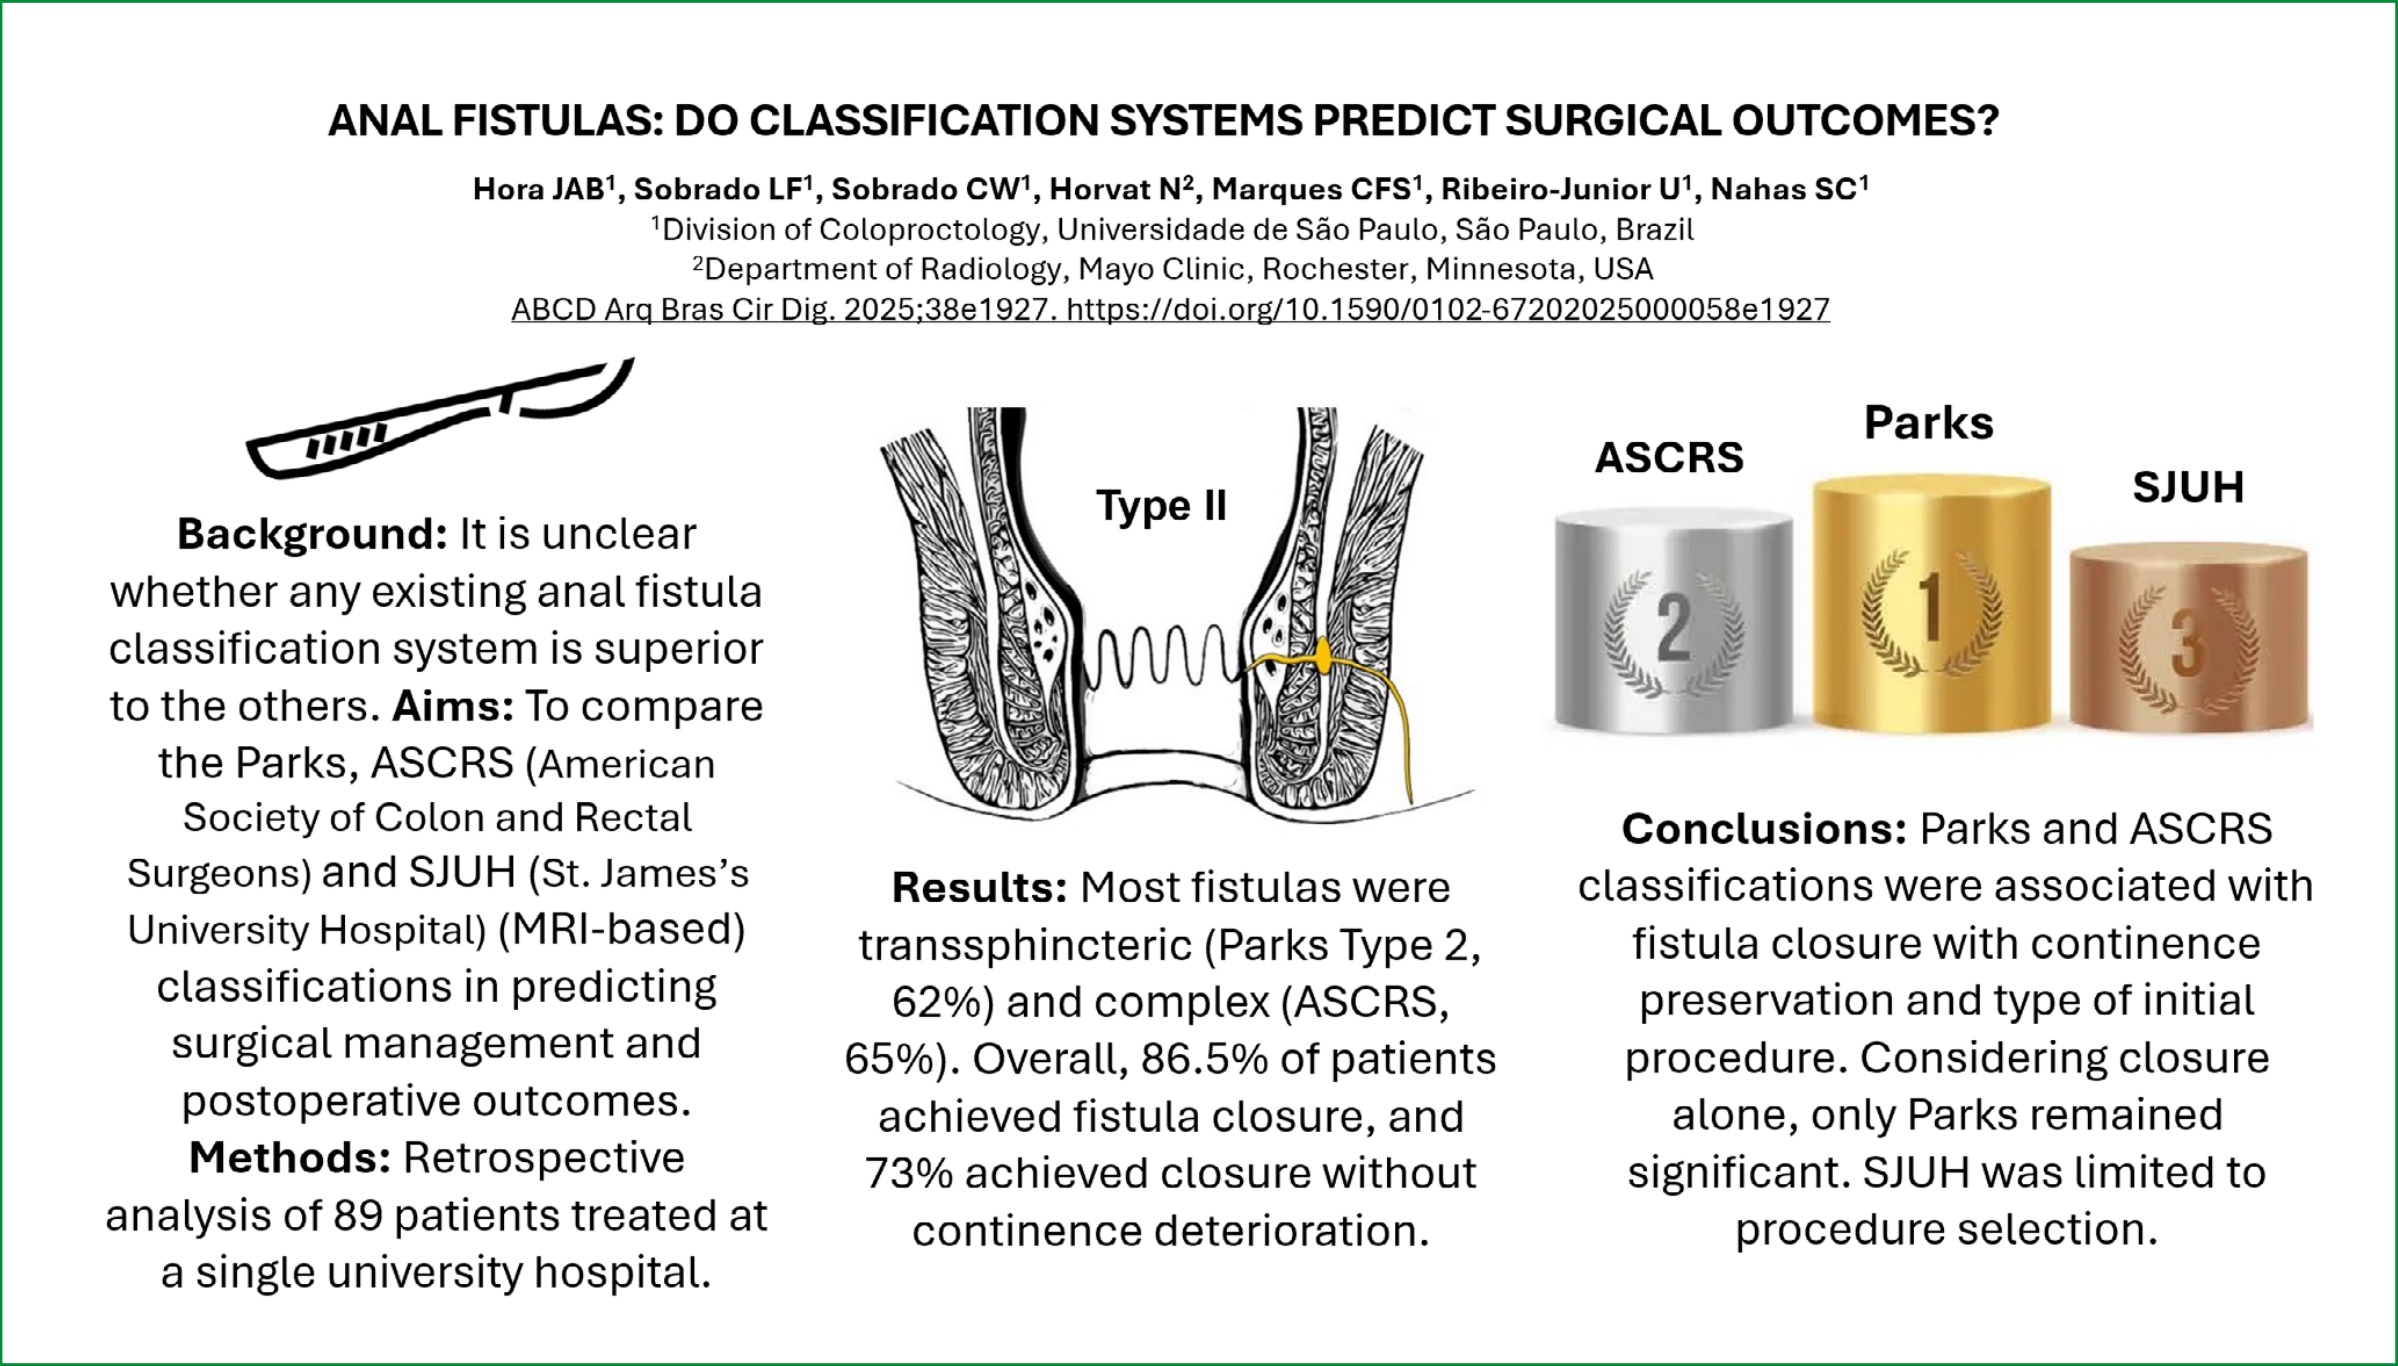
Anal fistulas remain challenging in colorectal surgery, with recurrence and postoperative incontinence common despite advances in treatment. Multiple classification systems exist, but their predictive value for surgical and functional outcomes is unclear.
The aim of this study was to compare Parks, American Society of Colon and Rectal Surgeons (ASCRS), and St. James’s University Hospital (SJUH) MRI-based classifications in predicting surgical outcomes, including continence preservation.
Retrospective analysis of 89 patients undergoing definitive surgical treatment for anorectal fistulas at a single referral center (2012–2019). Exclusions included rectovaginal fistulas, Crohn’s disease, or prior pelvic radiotherapy. Fistulas were classified using Parks, ASCRS, and, when available, SJUH (n=49). Outcomes included the number of procedures, type of initial procedure, fistula closure, and closure without continence deterioration. Continence was assessed using the Cleveland Clinic Jorge-Wexner score.
Most fistulas were transsphincteric (Parks Type 2, 62%) and complex (ASCRS, 65%). Overall, 86.5% achieved fistula closure, and 73% achieved closure without continence deterioration. Parks and ASCRS were significantly associated with fistula closure with continence preservation (p=0.008 and 0.007, respectively) and type of initial procedure. Parks remained significant when considering closure alone (p=0.005), while ASCRS showed a borderline association (p=0.051). SJUH classification was associated only with procedure selection.
Parks and ASCRS classifications were associated with fistula closure with continence preservation and type of initial procedure. Considering closure alone, only Parks remained significant. SJUH was limited to procedure selection. Overall, Parks and ASCRS guide surgical planning and prediction of functional outcomes, with Parks slightly more sensitive.

Inguinal hernia is the most frequently diagnosed hernia and affects approximately one-third of the male population. Several risk factors have been identified, including advanced age, limited physical activity, smoking, and increased intra-abdominal pressure, among others.
The aim of the study was to determine whether constipation is a risk factor for inguinal hernia in the adult population.
A case-control study was conducted at the Department of Surgery of one hospital in the north of Peru, including 121 patients with a confirmed diagnosis of inguinal hernia as cases and 242 patients without such a diagnosis as controls. Inclusion and exclusion criteria were applied, and data were collected through individual interviews using a structured questionnaire that addressed clinical aspects, lifestyles, and the presence of constipation, assessed according to the Rome IV criteria.
Results:
The results revealed significant differences between the groups of patients with and without inguinal hernia in terms of age, sex, and anthropometric characteristics. In addition, statistically significant associations were found between the presence of an inguinal hernia and type 2 diabetes, smoking, and constipation. A multivariate analysis showed that age, male sex, body mass index, high blood pressure, and constipation were significant and independent factors associated with the presence of inguinal hernia.
Constipation is a significant risk factor for inguinal hernia in the adult population. These results support the importance of considering constipation as a risk factor in the evaluation and management of patients with inguinal hernia, highlighting the relevance of adequate clinical care in this group of patients.
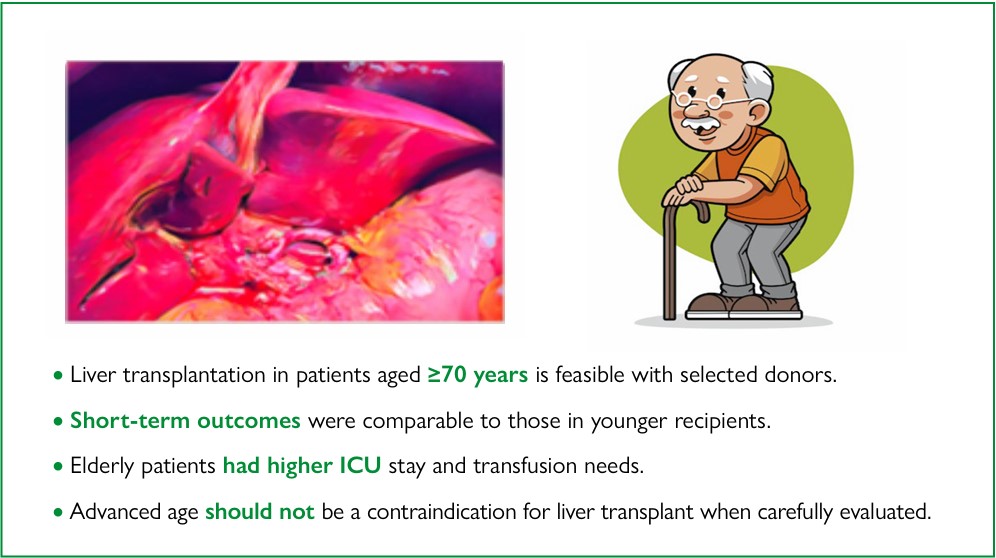
Liver transplantation (LT) is increasingly recognized as a treatment option for various diseases affecting a growing elderly population. However, its use in patients over 70 years of age remains controversial in centers with suboptimal outcomes or high waitlist mortality.
The aim of this study was to evaluate the effectiveness of LT as a treatment option for elderly patients aged 70 years or older, in comparison with younger recipients.
This retrospective study was conducted based on medical record data from 309 liver transplant recipients treated by the same surgical team across three hospitals — two located in São Paulo, São Paulo state (SP) and one in Rio Branco, Acre state (AC). Patients were divided into two groups for comparison: those aged up to 69 years (Group I) and those aged 70 years or older (Group II).
Donor characteristics were similar between the two groups, except for a higher norepinephrine dose in Group I (p<0.05). Group II showed greater transfusion requirements and longer intensive care unit (ICU) stays (p<0.05), as well as higher rates of malnutrition and comorbidities. Notably, 90-day survival was comparable between the groups.
Patients aged 70 years or older can achieve outcomes comparable to those of younger recipients, provided they receive grafts from carefully selected donors. This population should not be excluded from transplant waitlists, and specific allocation policies or scoring adjustments should be considered to ensure equitable access.
A retrospective analysis of liver transplants was performed, comparing patients over and under 70 years of age. The elderly group was transplanted with careful donor selection and obtained results comparable to those of the younger group.
This study aims to show that elderly patients over 70 years of age can have good results after liver transplantation, comparable to patients under 70 years of age, with good donor selection and perhaps additional points to favor their position on the waiting list.
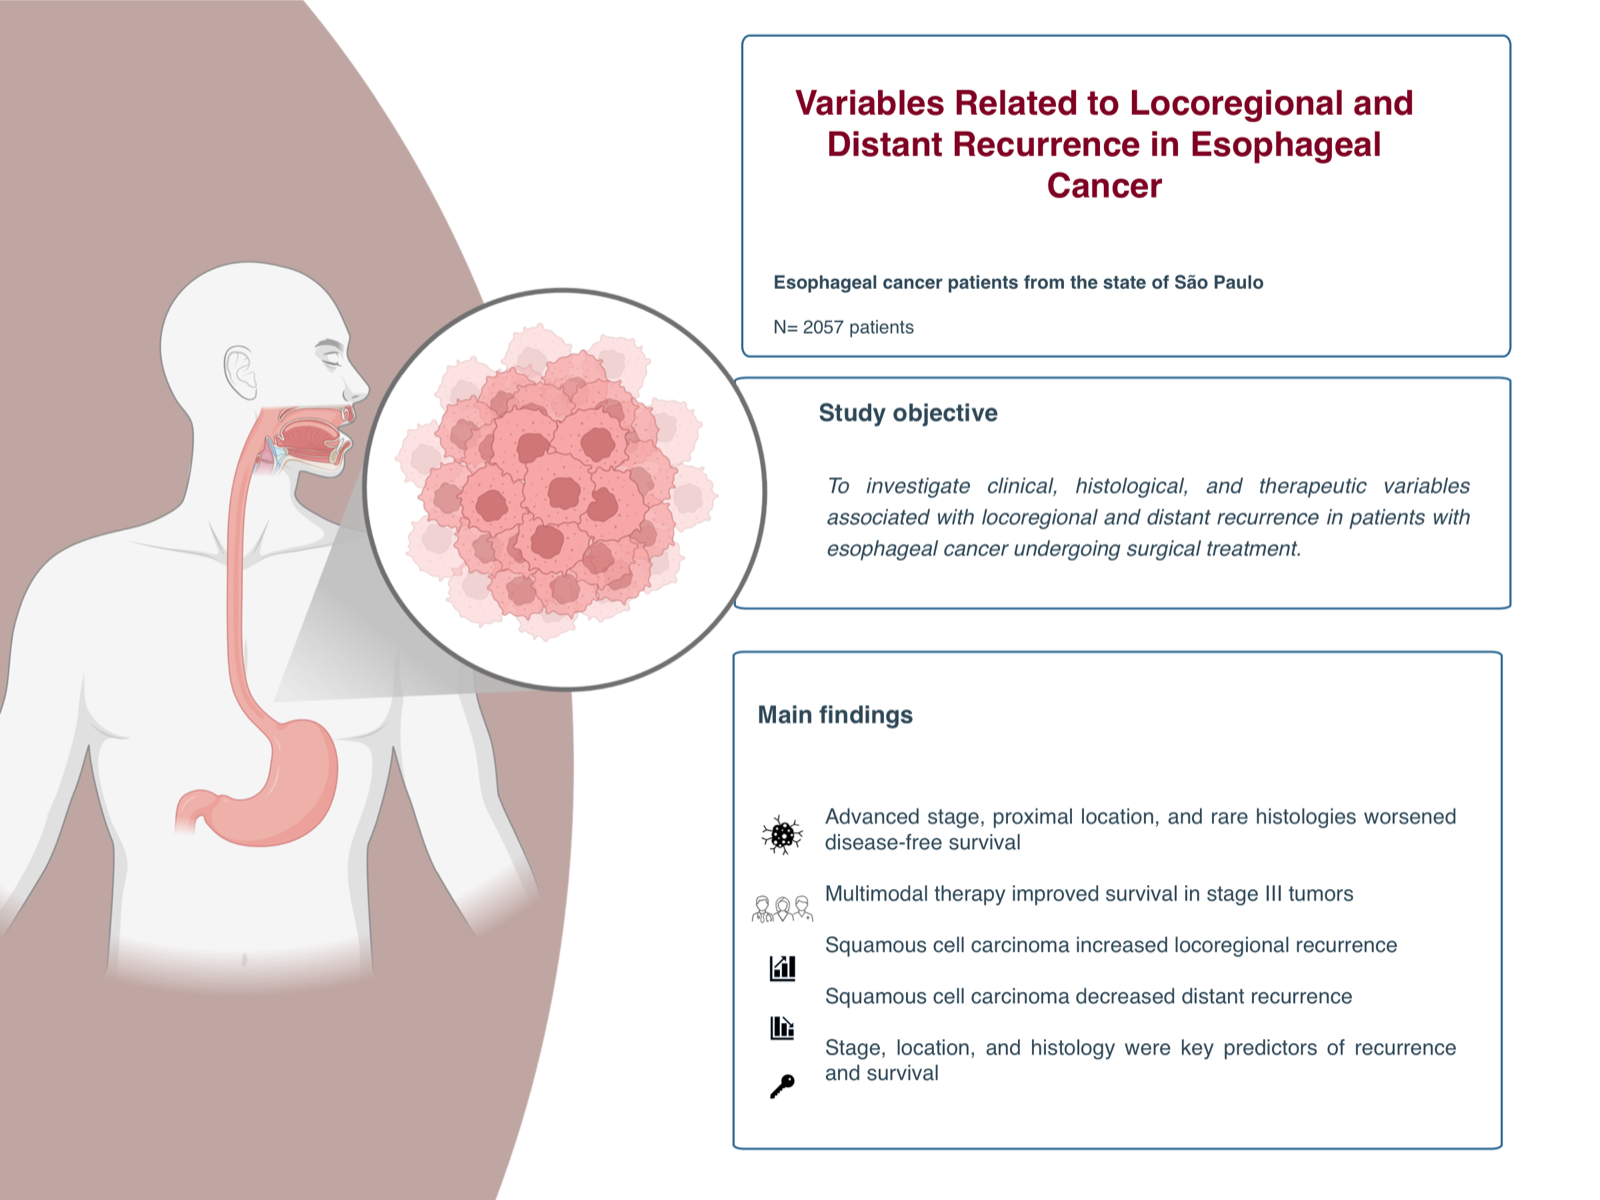
Esophageal cancer remains one of the most aggressive malignancies of the gastrointestinal tract, with high rates of recurrence and mortality despite curative-intent surgery and adjuvant therapies. Identifying factors associated with recurrence is crucial for improving outcomes and guiding personalized treatment.
The aim of this study was to evaluate pretreatment and treatment-related variables associated with recurrence in patients with esophageal cancer undergoing surgical resection.
This retrospective study analyzed data from patients with stage I–III esophageal carcinoma who underwent esophagectomy between 2000 and 2025, using the Fundação Oncocentro de São Paulo (FOSP) database. Clinical, histological, and treatment-related variables were evaluated. Disease-free survival and recurrence patterns were assessed using Cox proportional hazards models and Fine–Gray subdistribution hazard models.
A total of 2,057 patients were included, with a mean follow-up of 36.5 months (±44.8). In the multivariate analysis, advanced tumor stage (stage II: HR 1.68, 95%CI 1.21–2.33; stage III: HR 3.23, 95%CI 2.29–4.56; both p<0.01), location (middle esophagus: HR 1.31, 95%CI 1.11–1.54; p=0.001; upper esophagus: HR 1.54, 95%CI 1.21–1.96; p<0.001), and histological subtype (rare histologies: HR 2.17, 95%CI 1.35–3.49; p=0.001) were associated with worse disease-free survival. Multimodal therapy improved disease-free survival (HR 0.40, 95%CI 0.24–0.66) in stage III tumors. Squamous cell carcinoma was independently associated with locoregional recurrence (SHR 1.52, 95%CI 1.05–2.20; p=0.027). For distant recurrence, squamous cell carcinoma showed a protective effect (SHR 0.52, 95%CI 0.31–0.88; p=0.015), while high tumor grade (grade II: SHR 3.65, 95%CI 1.98–6.72; p<0.001) was associated with an increased risk. Multimodal treatments influenced recurrence patterns but did not independently predict outcomes after adjustment.
Tumor stage, location, and histology were strong predictors of disease-free survival after surgery for esophageal cancer. Histological subtypes significantly influenced recurrence patterns. Squamous cell carcinoma was associated with a higher risk of locoregional recurrence but a lower risk of distant metastasis compared to adenocarcinoma. Multimodal therapy demonstrated a protective effect in stage III disease.
One of the primary complications associated with large incisions in abdominal surgery is the increased risk of fascial closure rupture and incisional hernia development. The choice of the fascial closure method and closing with minimal tension and trauma is crucial for optimal results, emphasizing the importance of uniform pressure along the suture line to withstand intra-abdominal pressure.
To evaluate the resistance to pressure and tension of stapled and sutured hand-sewn fascial closure in the abdominal wall.
Nine abdominal wall flaps from human cadavers and 12 pigs were used for the experimentation. An abdominal defect was induced after the resection of the abdominal wall and the creation of a flap in the cadaveric model and after performing a midline incision in the porcine models. The models were randomized into three groups. Group 1 was treated with a one-layer hand-sewn small bite suture, Group 2 was treated with a two-layer hand-sewn small bite suture, and Group 3 was treated with a two-layer stapled closure. Tension measurements were assessed in cadaveric models, and intra-abdominal pressure was measured in porcine models.
In the human cadaveric model, the median threshold for fascial rupture was 300N (300-350) in Group 1, 400N (350-500) in Group 2, and 350N (300-380) in Group 3. Statistical comparisons revealed non-significant differences between Group 1 and Group 2 (p=0.072, p>0.05), Group 1 and Group 3 (p=0.346, p>0.05), and Group 2 and Group 3 (p=0.184, p>0.05). For porcine subjects, Group 1 showed a median pressure of 80 mmHg (85-105), Group 2 had a median of 92.5 mmHg (65-95), and Group 3 had a median of 102.5 mmHg (80-135). Statistical comparisons indicated non-significant differences between Group 1 and Group 2 (p=0.243, p>0.05), Group 1 and Group 3 (p=0.468, p>0.05), and Group 2 and Group 3 (p=0.083, p>0.05).
Stapled and conventional suturing resist similar pressure and tension thresholds.

🎥 Watch the supplementary video: surgical technique
↗
Central pancreatectomy (CP) is a parenchyma-sparing alternative to standard resections for benign or low-grade lesions of the pancreatic neck. While it aims to preserve endocrine and exocrine function, it is associated with significant technical complexity and high rates of postoperative pancreatic fistula (POPF).
To analyze the CP at a single high-volume Brazilian center.
A retrospective analysis of a prospectively maintained database was conducted. All patients undergoing CP at a single high-volume Brazilian center between January 2009 and December 2024 were included. Data on demographics, operative details, pathology, complications (International Study Group of Pancreatic Surgery – ISGPS/Clavien-Dindo criteria), and long-term pancreatic function were collected.
Twenty-two patients underwent CP (mean age 54 years, 72% female). The majority of lesions were cystic (50%) or neuroendocrine tumors (36.4%). The POPF rate was 86.4%, all Grade B, most managed conservatively via prolonged drainage. No Grade C fistulas, postoperative hemorrhages, or mortality occurred. Delayed gastric emptying occurred in 22.7%. After a median follow-up of 5.59 years, endocrine insufficiency developed in 9% of patients without prior diabetes (none insulin-dependent), and exocrine insufficiency in 13.6%. Only one locoregional recurrence was observed (isolated metastasis).
This first Latin American series demonstrates that central pancreatectomy is a feasible and effective parenchyma-sparing procedure. It provides excellent long-term preservation of pancreatic function with low severe morbidity, despite high rates of manageable POPF. These outcomes support its role as a valuable surgical option for selected patients in experienced centers.
Liver transplantation is a complex and valuable therapy. However, complications that burden postoperative quality of life, such as incisional hernia, are to be better elucidated, such as risk factors and prophylactic measures.
This study aimed to define the rate of incisional hernia in patients who underwent liver transplantation in a population in southern Brazil and to assess the related risk factors in order to establish measures for prior optimization and specific prophylactic care in the future.
Patients undergoing adult Liver transplantation from January 2004 to November 2020 were retrospectively analyzed, assessing demographic features, surgical outcomes, and predisposing factors.
Among 261 liver transplantation patients included, incisional hernia was diagnosed in 71 (27.2%). Of the 71 incisional hernia patients, 28 (39.4%) developed IH during the first post-transplant. Majority of the patients were male (52/71, 73.2%); of the 71 patients, 52 had hepatitis C virus (HCV) and 33 (46.5%) had hepatocellular carcinoma (HCC). Male gender (p=0.044), diabetes mellitus (p=0.008), and acute cellular rejection (p<0.001) were risk factors for IH. In all, 28 (39.4%) patients were submitted for hernia repair with mesh, with a recurrence rate of 17.8%.
Incisional hernia after liver transplantation is a relatively common problem associated with male gender, diabetes, and acute cellular rejection. This is a problem that should not be trivialized in view of the complexity of liver transplantation, as it can lead to a reduction in quality of life as well as jeopardize late liver transplantation results and lead to incarceration and strangulation.
The development of an incisional hernia is a common complication following laparotomy. It also has an important economic impact on healthcare systems and social security budget. The mesh reinforcement of the abdominal wall was an important advancement to increase the success of the repairs and reduce its long-term recurrence. The two most common locations for mesh placement in ventral hernia repairs include the premuscular (onlay technique) and retromuscular planes (sublay technique). However, until now, there is no consensus in the literature about the ideal location of the mesh.
The aim of this study was to compare the two most common incisional hernia repair techniques (onlay and sublay) with regard to the complication rate within the first 30 days of postoperative care.
This study analyzes 115 patients who underwent either onlay or sublay incisional hernia repairs and evaluates the 30-day postoperative surgical site occurrences and hernia recurrence for each technique.
We found no difference in the results between the groups, except in seroma formation, which was higher in patients submitted to the sublay technique, probably due to the lower rate of drain placement in this group.
Both techniques of mesh placement seem to be adequate in the repair of incisional hernias, with no major difference in surgical site occurrences.




Developed by Surya MKT