

Achalasia is an esophageal motility disorder, and myotomy is one of the most used treatment techniques. However, symptom persistence or recurrence occurs in 9 to 20% of cases.
This study aims to provide a practical approach for managing the recurrence or persistence of achalasia symptoms after myotomy.
A critical review was performed to gather evidence for a rational approach for managing the recurrence or persistence of achalasia symptoms after myotomy.
To properly manage an achalasia patient with significant symptoms after myotomy, such as dysphagia, regurgitation, thoracic pain, and weight loss, it is necessary to classify symptoms, stratify severity, perform appropriate tests, and define a treatment strategy. A systematic differential diagnosis workup is essential to cover the main etiologies of symptoms recurrence or persistence after myotomy. Upper digestive endoscopy and dynamic digital radiography are the main tests that can be applied for investigation. The treatment options include endoscopic dilation, peroral endoscopic myotomy, redo surgery, and esophagectomy, and the decision should be based on the patient’s individual characteristics.
A good clinical evaluation and the use of proper tests jointly with a rational assessment, are essential for the management of symptoms recurrence or persistence after achalasia myotomy.
The field of medicine has always been at the forefront of technological innovation, constantly seeking new strategies to diagnose, treat, and prevent diseases. Guidelines for clinical practice to orientate medical teams regarding diagnosis, treatment, and prevention measures have increased over the years. The purpose is to gather the most medical knowledge to construct an orientation for practice. Evidence-based guidelines follow several main characteristics of a systematic review, including systematic and unbiased search, selection, and extraction of the source of evidence. In recent years, the rapid advancement of artificial intelligence has provided clinicians and patients with access to personalized, data-driven insights, support and new opportunities for healthcare professionals to improve patient outcomes, increase efficiency, and reduce costs. One of the most exciting developments in Artificial Intelligence has been the emergence of chatbots. A chatbot is a computer program used to simulate conversations with human users. Recently, OpenAI, a research organization focused on machine learning, developed ChatGPT, a large language model that generates human-like text. ChatGPT uses a type of AI known as a deep learning model. ChatGPT can quickly search and select pieces of evidence through numerous databases to provide answers to complex questions, reducing the time and effort required to research a particular topic manually. Consequently, language models can accelerate the creation of clinical practice guidelines. While there is no doubt that ChatGPT has the potential to revolutionize the way healthcare is delivered, it is essential to note that it should not be used as a substitute for human healthcare professionals. Instead, ChatGPT should be considered a tool that can be used to augment and support the work of healthcare professionals, helping them to provide better care to their patients.
Although the presence of synchronous colorectal liver metastases (CRLM) represents an important prognostic factor for recurrence-free survival (RFS) and overall survival (OS), the definitions of synchronicity are variable in the literature, including metastases at the time of diagnosis, or even before the diagnostic of the primary site of colorectal cancer (CRC), until either six or 12 months after the time of diagnosis, according to the author of each study. Simultaneous approaches to treat CRC and CRLM seem to be safe for patients carefully selected without jeopardizing oncologic outcomes, with similar complication rates, shorter hospital length of stay, and operation times even for major hepatectomies. However, there is no consensus about the optimal timing to approach the primary tumor and CRLM, whether simultaneously or staged, and both performance status and the presence of symptoms play important roles in the treatment sequence, perhaps avoiding two high-risk procedures at the same time.
The classification of resectability for pancreatic ductal adenocarcinoma is crucial in guiding treatment strategies. A recent system including anatomic (A), biological (B), and conditional (C) factors has been used to select the patients who underwent pancreatoduodenectomy, and centralization has been associated with low mortality and defined as a critical determinant of surgical outcomes. A comprehensive literature review assessed the impact of incorporating the ABC criteria in patients with pancreatic ductal adenocarcinoma. Incorporating biological and conditional criteria for patients with pancreatic ductal adenocarcinoma could enhance patient stratification accuracy and improve clinical outcomes and survival.
Pancreatic cancer is still a terrifying condition that has a high mortality rate due to its rapid progression and treatment complexity. However, there is still no consensus on what the gold standard of treatment for locally advanced pancreatic cancer (LAPC) is.
The aim of this study was to review the current evidence-based data on treatment strategies for LAPC, comparing pancreatoduodenectomy with vascular reconstruction (PDVR) and chemotherapy alone (CA).
This systematic review was performed according to the PRISMA 2020 guidelines. Overall survival (OS) was the primary endpoint, while progression-free survival (PFS) was the secondary endpoint. The included studies were published between 2013 and 2023.
A total of 16 relevant papers were found in the literature search. The median PFS duration for CA varied from 3.22 to 11.7 months, whereas the median overall survival (mOS) varied from 5.95 to 23.0 months. The mOS ranged from 12.7 to 24.9 months and the median PFS time ranged from 8.5 to 22.5 months for patients submitted to neoadjuvant therapy followed by PDVR.
LAPC presents worse outcomes when patients are submitted to CA with gemcitabine only, or when patients undergo upfront PDVR.
Although the presence of synchronous colorectal liver metastases (CRLM) represents an important prognostic factor for recurrence-free survival (RFS) and overall survival (OS), the definitions of synchronicity are variable in the literature, including metastases at the time of diagnosis, or even before the diagnostic of the primary site of colorectal cancer (CRC), until either six or 12 months after the time of diagnosis, according to the author of each study. Simultaneous approaches to treat CRC and CRLM seem to be safe for patients carefully selected without jeopardizing oncologic outcomes, with similar complication rates, shorter hospital length of stay, and operation times even for major hepatectomies. However, there is no consensus about the optimal timing to approach the primary tumor and CRLM, whether simultaneously or staged, and both performance status and the presence of symptoms play important roles in the treatment sequence, perhaps avoiding two high-risk procedures at the same time.
The presence of synchronous colorectal liver metastases represents an important prognostic factor for recurrence-free survival and overall survival, the definitions of synchronicity are variable in the literature, including metastases at the time of diagnosis, or even before the diagnostic of the primary site of colorectal cancer, and until either six or 12 months after the time of diagnosis, according to the authors of the studies.
Simultaneous approaches to treat colorectal cancer and colorectal liver metastases seem to be safe for patients carefully selected without jeopardizing oncologic outcomes, with similar complication rates, shorter length of stay and operation times even for major hepatectomies. However, there is no consensus about the optimal timing to approach the primary tumor and colorectal liver metastases, whether simultaneously or staged, and both performance status and presence of symptoms play important roles in the treatment sequence, perhaps avoiding two high-risk procedures at the same time
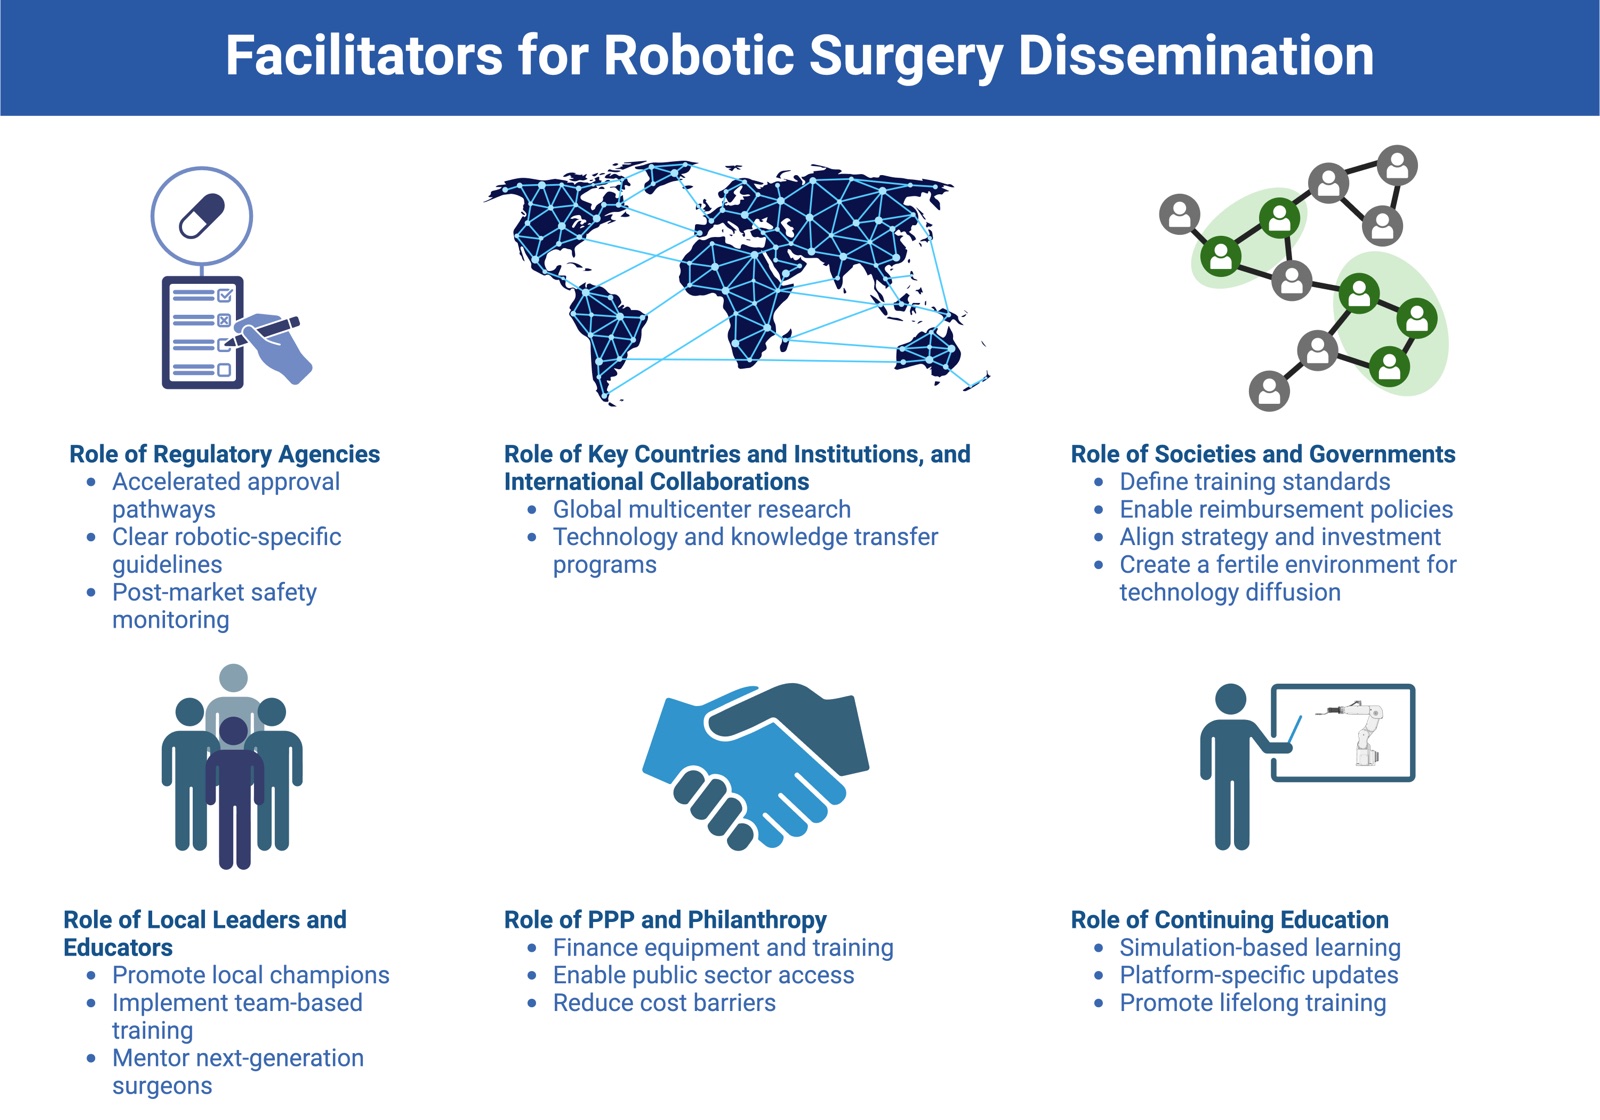
The global adoption of robotic surgery has advanced rapidly in high-income countries, yet its diffusion remains limited in resource-constrained settings due to financial, infrastructural, and educational barriers. As surgical technology evolves, there is an urgent need to promote countries’ equitable access to robotic platforms worldwide.
The aim of this study was to analyze global strategies employed to promote the diffusion of robotic surgery, with a particular focus on overcoming barriers in resource-limited settings, and to provide practical insights that can guide its equitable and sustainable implementation.
This study is a multinational, policy-oriented integrative review conducted under the guidance of the Research Committee of the Society for Surgery of the Alimentary Tract in the USA (SSAT). The study integrates a bibliometric analysis, a literature review, and expert insights from diverse healthcare environments. Contributions were gathered from SSAT members.
Robotic platforms are predominantly concentrated in North America, Western Europe, and Eastern Asia, with the USA hosting nearly 60% of all installations. Research output is similarly skewed, with few countries and institutions producing most clinical trials. Key barriers to diffusion include high costs, lack of infrastructure, limited training capacity, regulatory hurdles, and resistance among surgeons. Facilitators include public–private partnerships, philanthropic support, technology transfer, simulation platforms, and curriculum integration by professional societies.
Achieving global equity in robotic surgery requires coordinated action across research, education, clinical practice, policy, and infrastructure. Global cooperation and innovation in implementation strategies can help bridge the current disparities and promote safe, cost-effective surgical care in underserved regions, improving patient outcomes.
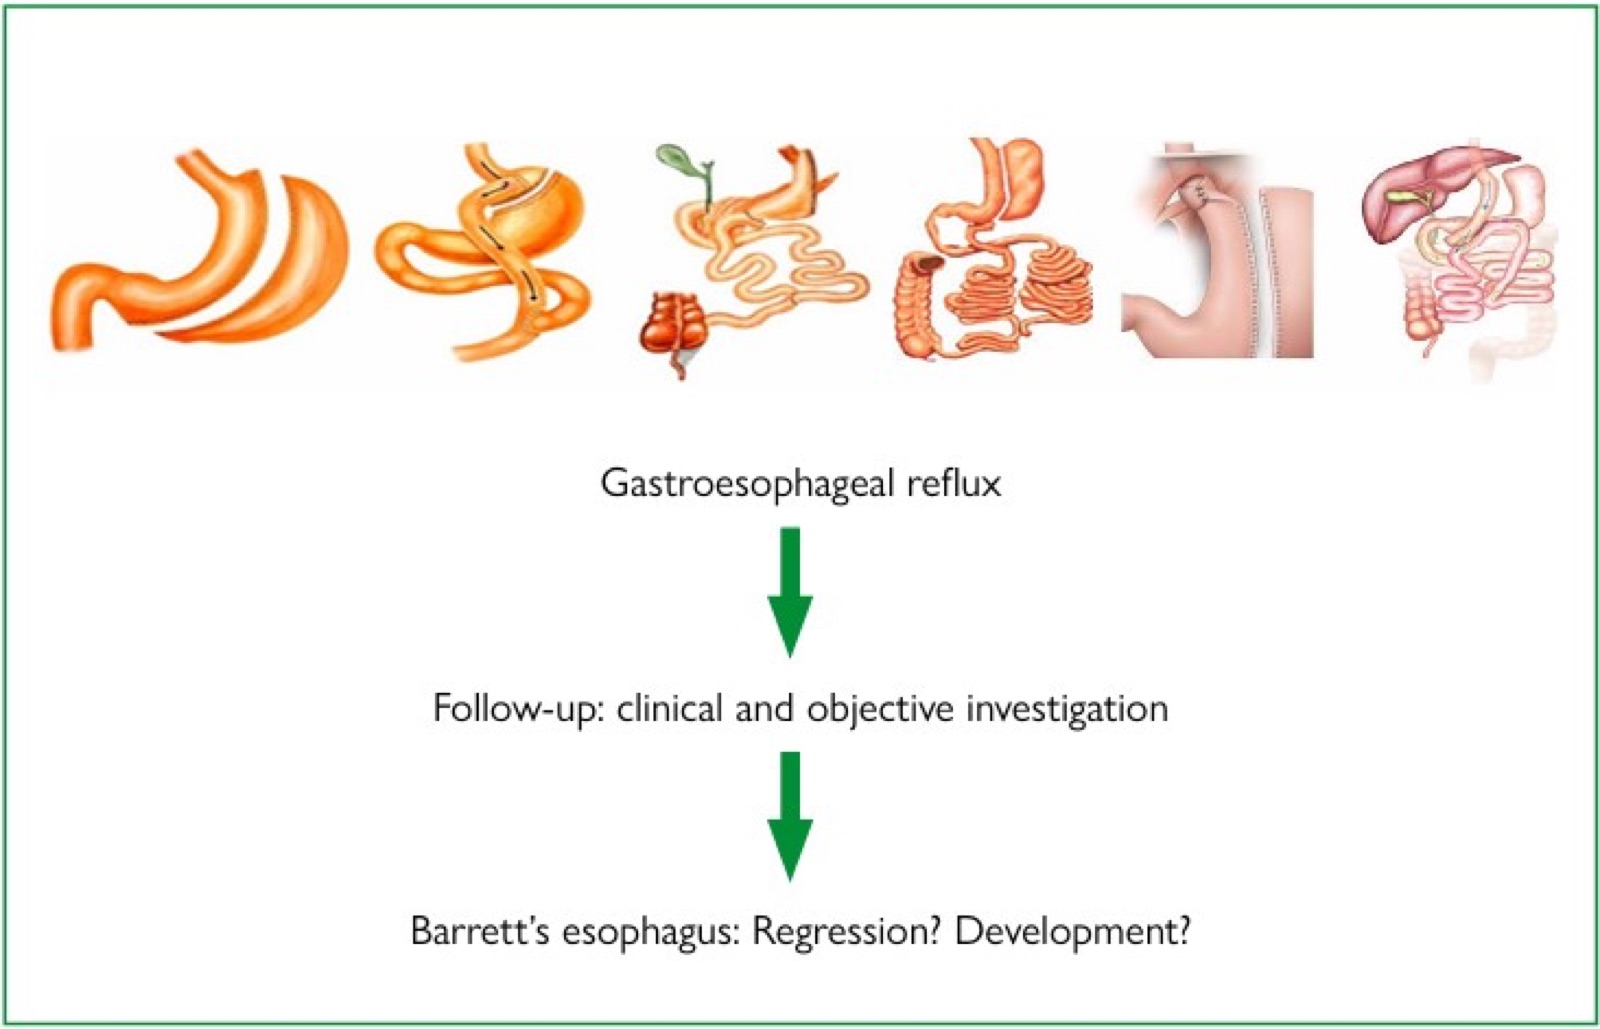
Studies have investigated the incidence of gastroesophageal reflux disease (GERD) and Barrett’s esophagus (BE) after common bariatric surgeries. However, many of these studies have bias or limitations. Therefore, it is crucial to determine the true incidence of GERD in long-term follow-ups (FUs) post-surgery.
The aim of this study was to review and summarize long-term data regarding the incidence of post-surgical GERD and BE after various bariatric procedures, discuss the characteristics of current information available, and establish the need for future studies to determine objective functional outcomes that have not yet been reported.
A narrative review was conducted using multiple electronic databases, including the review of 15 meta-analyses and over 200 articles.
The quality of studies analyzing GERD and BE following bariatric surgery varies widely. Some papers provide detailed outcomes, while others offer limited information. The reported rate of de novo postoperative GERD development after sleeve gastrectomy varies from 4.06 to 74.7% (mean=33.8±19.1), and the incidence of BE ranges from 0.2 to 27% (mean=8.2±7.5). After Roux-en-Y gastric bypass (RYGB), similar variability is observed, with BE incidence ranging from 1.6 to 17.5% (mean=7.5±5.9). In the case of one-anastomosis gastric bypass (OAGB), scarce information is available and most reports are incomplete. The incidence of erosive esophagitis ranges from 15 to 70%, with BE incidence reported in only two papers (1–9.5%). For procedures such as single-anastomosis duodeno-ileal bypass with sleeve gastrectomy (SADI-S), fundoplication-sleeve, or sleeve bipartition, few specific data are available, with most reports limited to symptoms and lacking findings such as esophagitis, hiatal hernia, or BE.
This revision provides evidence that SG may indeed lead to an increased risk of BE. Numerous studies suggest that RYGB protects against BE. Other bariatric procedures must be extensively evaluated. Relatively low quality of available literature on this topic was observed; therefore, well-controlled prospective studies with long-term FUs are necessary to fully understand the effect of bariatric surgery on BE.
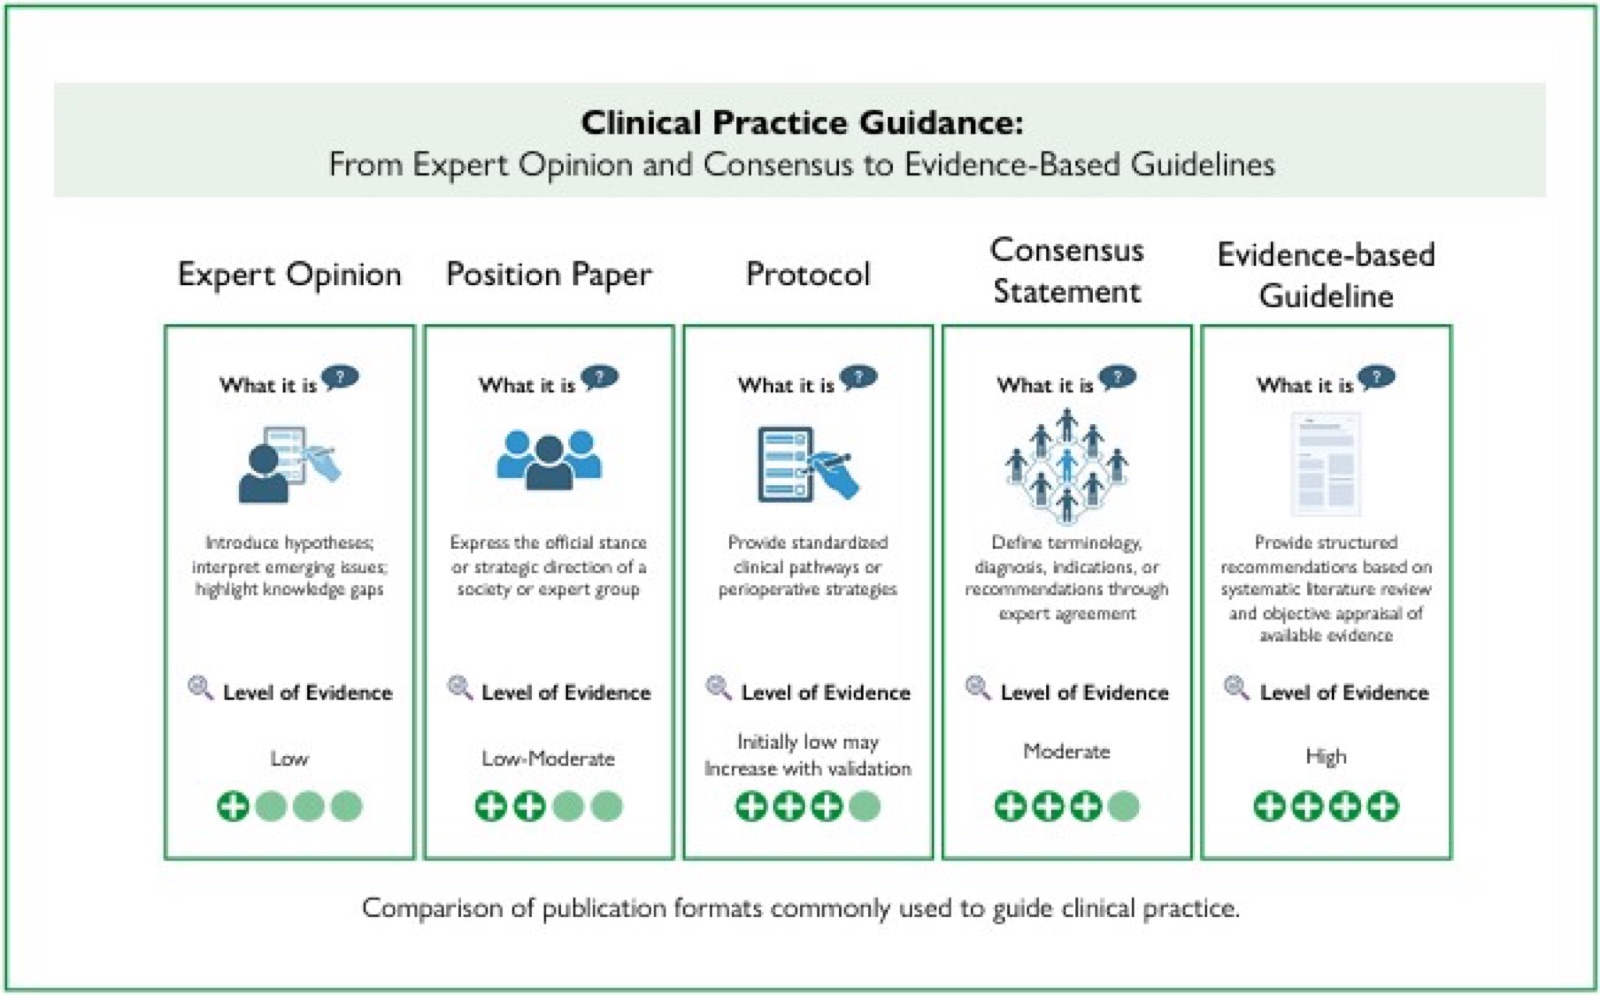
The growth of primary research in digestive surgery has led to an increasing need for structured interpretation and application to clinical practice. Guidance documents have become essential tools for decision-making. However, the terminology surrounding clinical guidance documents is frequently inconsistent, and different formats are often used interchangeably. Although review articles synthesize available evidence, they do not constitute clinical guidance unless their findings are interpreted through a framework explicitly oriented toward patient care, applicability, and decision-making. This review article clarifies the conceptual distinctions between expert opinion, consensus statements, position papers, protocols, and evidence-based guidelines. No single guidance format is universally superior, and each has its appropriate context. In digestive surgery, where randomized trials are often difficult to perform and evidence gaps remain frequent, structured interpretation is indispensable. As technology advances and real-world data become increasingly available, new methodological tools — including artificial intelligence and living systematic reviews — may enhance reproducibility and accelerate updates. Ultimately, clearer distinctions among guide orientations and greater methodological transparency may improve clinical judgment, stimulate research, and strengthen patient care in gastrointestinal surgery.
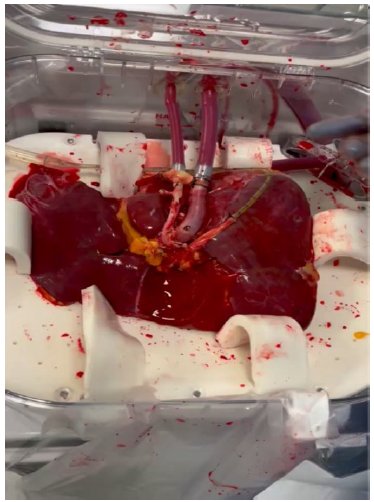
Despite the annual increase in liver transplants, a persistent disparity between suitable donors and recipients continues to challenge the transplant community. The introduction of machine perfusion emerged as a novel approach to organ preservation. This technique, which utilizes extended criteria donor grafts, is expected to reduce rejection rates and expand the donor pool. Its principle, like that of any ex vivo machine perfusion, is based on the continuous supply of nutrients and oxygen to maintain cellular metabolism while interrupting anaerobic processes. This helps prevent conditions such as ischemia-reperfusion injury, early graft dysfunction, and ischemic cholangiopathy, which can lead to graft loss and the need for retransplantation. There are two main modes of ex vivo machine perfusion: hypothermic and normothermic, differentiated by the operating temperature. Utilizing ex situ perfusion machines presents a promising opportunity to increase liver graft usage and reduce waitlist times. However, it is crucial to evaluate how much this technology would raise the overall cost of transplants. In Brazil, implementing a machine perfusion program may encounter unique challenges not seen in other countries. These challenges include limited access to the healthcare system for high-risk liver transplant candidates, long waiting lists, inadequate support for organ donors, reliance solely on deceased brain-dead donors, since donation after cardiac death is not ethically accepted, and geographical barriers.




Developed by Surya MKT